Skip to content

Last Updated: November 4, 2026
Quick Summary
Tesamorelin is a synthetic GHRH analog that stimulates the body’s own growth hormone release and is FDA-approved only for reducing excess visceral abdominal fat in adults with HIV-associated lipodystrophy. A 2026 meta-analysis found a 15.2% reduction in visceral adipose tissue over 26 weeks versus a 5.0% gain with placebo. It holds no FDA approval for general weight loss or anti-aging use.
- The FDA-approved dose is 2 mg injected subcutaneously once daily.
- Rotate injection sites at least two finger-widths from the navel and prior sites.
- Check baseline fasting glucose and A1c, repeat at 4 to 6 weeks, then every 3 months.
- A 52-week study showed visceral fat reduction and lean mass preserved in HIV lipodystrophy.
- Semaglutide reduces appetite and slows gastric emptying, while tesamorelin targets visceral fat.
Table of Contents
- What Tesamorelin Is and How It Targets Visceral Fat
- Tesamorelin Dosage: What the Label Says and What Users Report
- Tesamorelin Side Effects and Safety Profile
- Tesamorelin vs Semaglutide: Two Different Approaches to Fat Loss
- Who Is a Candidate and Who Should Avoid It
- Long-Term Safety and Lifestyle Integration
- Discussing Tesamorelin With a MedShape Physician
- Frequently Asked Questions
What Tesamorelin Is and How It Targets Visceral Fat
Tesamorelin is a synthetic peptide that mimics growth hormone-releasing hormone (GHRH). Its FDA approval is limited to a specific indication, described below. People often ask about tesamorelin in the same breath as GLP-1 drugs, and want to know whether it belongs in the same conversation.
The short answer: it partly does, and partly doesn’t. A 2026 meta-analysis of randomized controlled trials found that patients treated with tesamorelin saw a 15.2% reduction in visceral adipose tissue over 26 weeks, while the placebo group gained 5.0% (2026 tesamorelin meta-analysis). That is a real, measurable effect on the fat that sits around the organs, not the fat you can pinch.
Below, we’ll break down the mechanism, the approved use versus the off-label claims, and where the evidence actually stops. For a deeper same-topic read on how the peptide targets stubborn visceral fat, see our guide to tesamorelin and metabolic vitality.
The GHRH Analog Mechanism
Tesamorelin is a GHRH analog: a 44-amino-acid synthetic peptide that binds to receptors in the anterior pituitary gland and stimulates the body’s own production of endogenous growth hormone. That last part matters. Unlike injecting growth hormone directly, tesamorelin asks the pituitary to release GH on the body’s normal feedback loop, which raises insulin-like growth factor 1 (IGF-1) while keeping the safety profile more favorable than exogenous growth hormone (PubMed review of tesamorelin in HIV-associated lipodystrophy).
The visceral fat effect comes downstream of that GH pulse. Visceral adipose tissue responds to GH signaling, and the result in trials was a reduction in visceral fat alongside improvements in hepatic fat, lean body mass, and IGF-1 levels. The peptide’s molecular weight is 5135.9 g/mol, and it is supplied as a lyophilized powder requiring reconstitution before subcutaneous injection.
FDA-Approved Use vs. Off-Label Use
Here is the distinction most online content blurs: tesamorelin is FDA-approved under the brand name Egrifta specifically for reducing excess visceral abdominal fat in adults with HIV-associated lipodystrophy. It holds no FDA approval for general weight loss, anti-aging, or body recomposition in healthy adults.
That gap is where the marketing lives. The anti-aging and body-composition angle for non-HIV users remains preclinical and unproven, and the evidence for general fat loss is limited to small pilot studies and case reports without large-scale trials in healthy adults (RWA Center analysis of tesamorelin evidence). We tell patients plainly: approved for one population, studied in others, and not the same thing.
Tesamorelin Dosage: What the Label Says and What Users Report
The FDA-approved dose is 2 mg injected subcutaneously once daily, per the prescribing information summarized by Mayo Clinic’s tesamorelin drug reference. That is the number with trial data behind it.

Outside clinical use, dosing drifts. Data reported in October 2026 suggests most users find results between 0.25 mg and 1 mg per day, with 0.5 mg per day emerging as a common point (The ICN report on tesamorelin dosing). That is user-reported practice, not label guidance, and the two should never be treated as interchangeable.
Injection Technique and Site Rotation
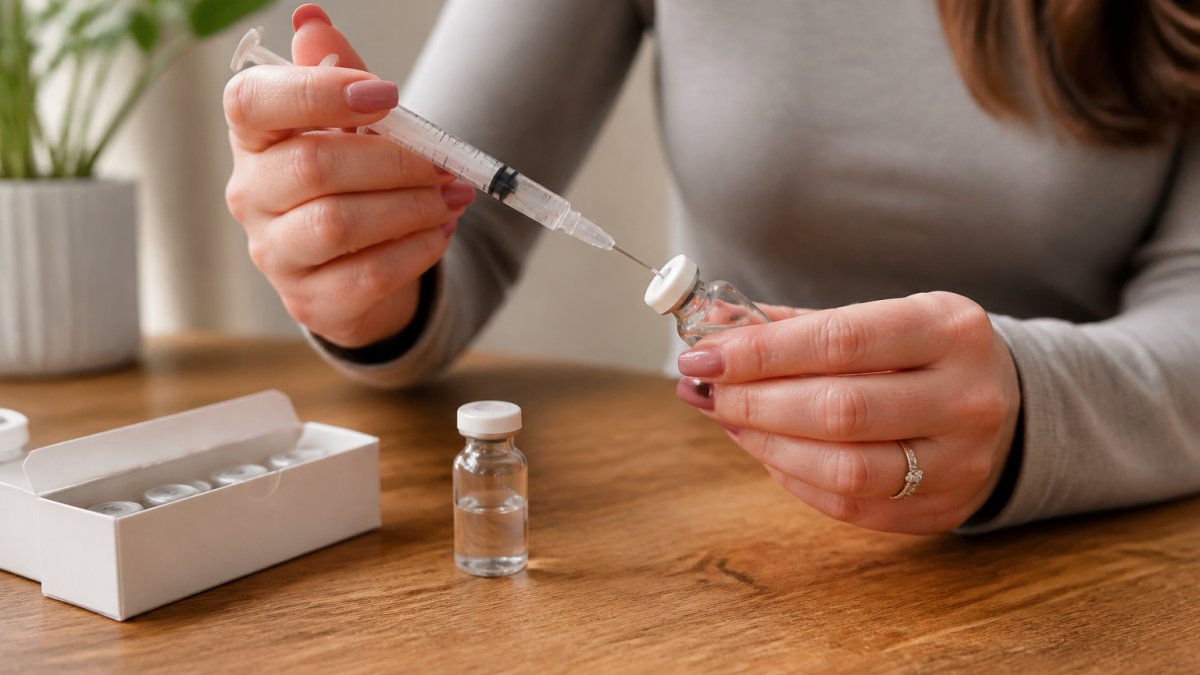
Tesamorelin goes subcutaneously, typically into the abdomen, and site rotation is not optional. Injecting the same spot daily causes lipohypertrophy, which is lumpy tissue that changes how the drug absorbs. Rotate between quadrants of the abdomen at least two finger-widths from the navel and from any previous site. Never inject into a lump, bruise, or scarred area.
Reconstitution matters too. The lyophilized powder must be mixed with the sterile water supplied with it, swirled gently rather than shaken, and stored per the label. A common mistake is mixing a large batch and letting it sit past its stability window.
Tesamorelin Side Effects and Safety Profile
Tesamorelin can cause side effects, and anyone considering it should review its full safety information with a physician.
The reaction that deserves real attention is glucose intolerance. Growth hormone signaling antagonizes insulin action, so tesamorelin can raise fasting glucose and hemoglobin A1c in susceptible patients. Clinical reviews indexed in NCBI note that glucose intolerance and diabetes can occur or worsen during therapy (NCBI clinical review of tesamorelin safety). A practical monitoring cadence most practitioners follow: baseline fasting glucose and A1c before the first injection, repeat at 4 to 6 weeks, then every 3 months once stable. Anyone with diabetes or pre-diabetes needs that plan documented before the first dose, not after.
Hypersensitivity reactions, including rash and urticaria, are possible. Contraindications and precautions for tesamorelin should be reviewed with a physician before starting treatment. Because GH and IGF-1 can promote tissue growth, new or worsening symptoms, carpal tunnel-type hand numbness, joint swelling, or visual changes, warrant prompt clinical review rather than dose escalation.
Fluid retention is the other event patients notice. Any new or persistent swelling should be evaluated by a physician.
For context on how this compares with the GLP-1 class, the side-effect burden is different in kind: tesamorelin does not cause the nausea, vomiting, or gastroparesis associated with semaglutide, but it does require glucose surveillance that GLP-1 therapy also demands. Our semaglutide versus tirzepatide comparison covers the GI profile of those agents.
Tesamorelin vs Semaglutide: Two Different Approaches to Fat Loss
These two drugs are not competitors in the way search results imply. Semaglutide is a GLP-1 receptor agonist that reduces appetite and slows gastric emptying, producing broad body-weight loss. Tesamorelin is a GHRH analog that targets visceral adipose tissue specifically, with a much narrower evidence base outside HIV-associated lipodystrophy.
| Feature | Tesamorelin | Semaglutide |
|---|---|---|
| Drug class | GHRH analog | GLP-1 receptor agonist |
| Primary mechanism | Stimulates endogenous GH release | Reduces appetite, slows gastric emptying |
| FDA-approved for | Visceral fat in HIV lipodystrophy | Type 2 diabetes and chronic weight management |
| Typical dosing | 2 mg subcutaneous daily | Weekly subcutaneous injection |
| Main safety concern | Glucose intolerance | GI side effects |
| Muscle preservation | Lean mass maintained in trials | Lean mass loss common |
If your goal is significant overall weight reduction, a GLP-1 pathway is the better-evidenced route, and our comparison of semaglutide versus tirzepatide covers how those two stack up. If the specific concern is deep visceral fat with muscle preservation, tesamorelin is the more targeted tool, and our breakdown of tesamorelin for visceral fat reduction goes further into that trade-off.
Who Is a Candidate and Who Should Avoid It
Candidacy for any peptide therapy is determined by a physician during a clinical evaluation.
Outside that group, candidacy is a judgment call made in a clinical setting, not a self-diagnosis. We look at metabolic markers, liver fat, glucose status, and whether the person has already failed more conventional approaches.
Long-Term Safety and Lifestyle Integration
Most content on tesamorelin stops at the 26-week trial endpoint. The more useful question, what happens over years of growth-hormone-axis modulation, is where the evidence thins, and where a supervised protocol matters most.
The longest controlled signal comes from a 52-week treatment study in HIV-associated lipodystrophy, which found that improvements in triglycerides and total cholesterol were maintained across the full period, with visceral adipose tissue reduction sustained and lean body mass preserved. A 2026 clinical efficacy meta-analysis associates tesamorelin with a triglyceride reduction of roughly 50 mg/dL alongside hepatic fat and lean mass improvements (2026 clinical efficacy meta-analysis). Beyond 52 weeks, the data are observational and extension-study based rather than large randomized trials, so the honest framing is: durable through one year in controlled data, plausible but less certain beyond that.
Long-term hormone-related safety questions are best reviewed with a physician, who can determine appropriate monitoring.
Lifestyle integration is not a soft add-on; it changes the arithmetic. Visceral fat responds to sleep duration, resistance training, protein intake, and alcohol reduction, and those inputs act on the same metabolic pathways the peptide touches. Lifestyle factors such as regular physical activity, adequate protein, limited alcohol and consistent sleep support overall metabolic health; a physician or nutrition specialist can help build a plan suited to you.
For the maintenance side, our science-backed guide to long-term weight loss covers the metabolic adaptation problem that trips up most people after the scale moves, and our breakdown of tesamorelin for visceral fat reduction goes deeper on the fat-distribution trade-off.
Discussing Tesamorelin With a MedShape Physician
A physician conversation can help clarify what tesamorelin is approved for and whether it is appropriate for you. Bring your glucose history, your current medications, and an honest account of what you have already tried.
MedShape Weight Loss Clinics provides physician-supervised programs customized to individual health needs. If you want to understand whether tesamorelin fits your situation, book a tesamorelin consultation and get a clinical answer instead of a forum one.
The peptide market rewards hype and punishes nuance, and tesamorelin sits right in the middle of that tension. Get a proper assessment with a licensed physician before deciding on any treatment. MedShape Weight Loss Clinics provides physician-supervised programs, customized to individual health needs, with telemedicine services available in all 50 states. Contact MedShape Weight Loss Clinics to learn more about the options that may fit your plan.
Frequently Asked Questions
Can tesamorelin get rid of belly fat?
Published research reports reductions in visceral fat, the fat stored deep around the organs, with tesamorelin in studied populations. Evidence for general weight loss in healthy adults is limited, and tesamorelin is not approved for that purpose.
Is tesamorelin similar to Ozempic?
Tesamorelin and semaglutide work through different mechanisms. Tesamorelin is a growth hormone-releasing hormone analog, while semaglutide is a GLP-1 receptor agonist. Check each drug’s official prescribing information for its approved uses and side effects.
Who should not take tesamorelin?
Whether tesamorelin is appropriate depends on your individual health history, so a full medical review with a physician is necessary before starting any therapy.
How does tesamorelin dosage work for non-clinical use?
Dosing should be determined by a physician. Self-adjusting dosage without medical supervision is not advised.